


Slide Decks on Parkinson’s Disease
Parkinson’s Disease (PD) is the second-most common neurodegenerative disorder, after Alzheimer’s Disease. PD is a chronic, progressive, neurodegenerative condition that mainly affects elderly people. The clinical effects of Parkinson’s Disease are visually obvious, but the underlying pathology of PD is still not fully understood.
In each slide deck, you will encounter a topic introduction and delve into essential concepts related to Parkinson’s disease. Our slide decks encompass a variety of subjects, including genetic risk factors for Parkinson’s disease, the challenges of managing non-motor symptoms, and motor complications such as dyskinesia and motor fluctuations.
Learn more about how Lewy bodies contribute to the pathophysiology of Parkinson’s Disease
History, Definitions, and Diagnosis
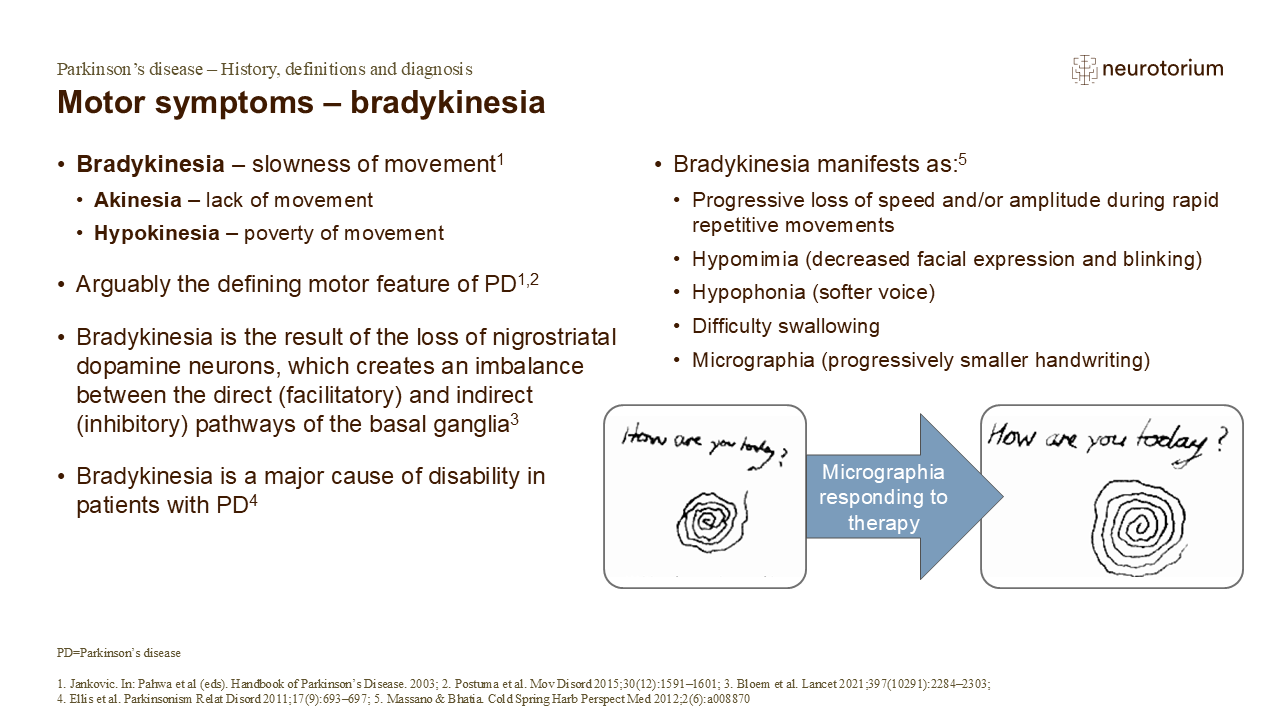
In this slide deck, basic PD concepts and definitions are explored. It includes infographics on the cardinal symptoms, diagnostic criteria, PD biomarkers, and commonly used scales in PD research. Go to the slide deck.

Epidemiology and Burden
This presentation covers the prevalence of Parkinson’s Disease across different global regions and describes the substantial burden the disease places on the patient and caregivers. Go to the slide deck.

Course, Natural History, and Prognosis
In this slide deck, the course, natural history and prognosis of PD are discussed, including infographics on prodromal PD as well as the stages of PD. Go to the slide deck.

Non-motor Symptom Complex and Comorbidities
Non-motor symptoms are reported by nearly all patients with Parkinson’s disease. In this slide deck, non-motor symptoms, quality of life and the comorbidities of Parkinson’s disease are discussed. Go to the slide deck.
Neurobiology and Aetiology
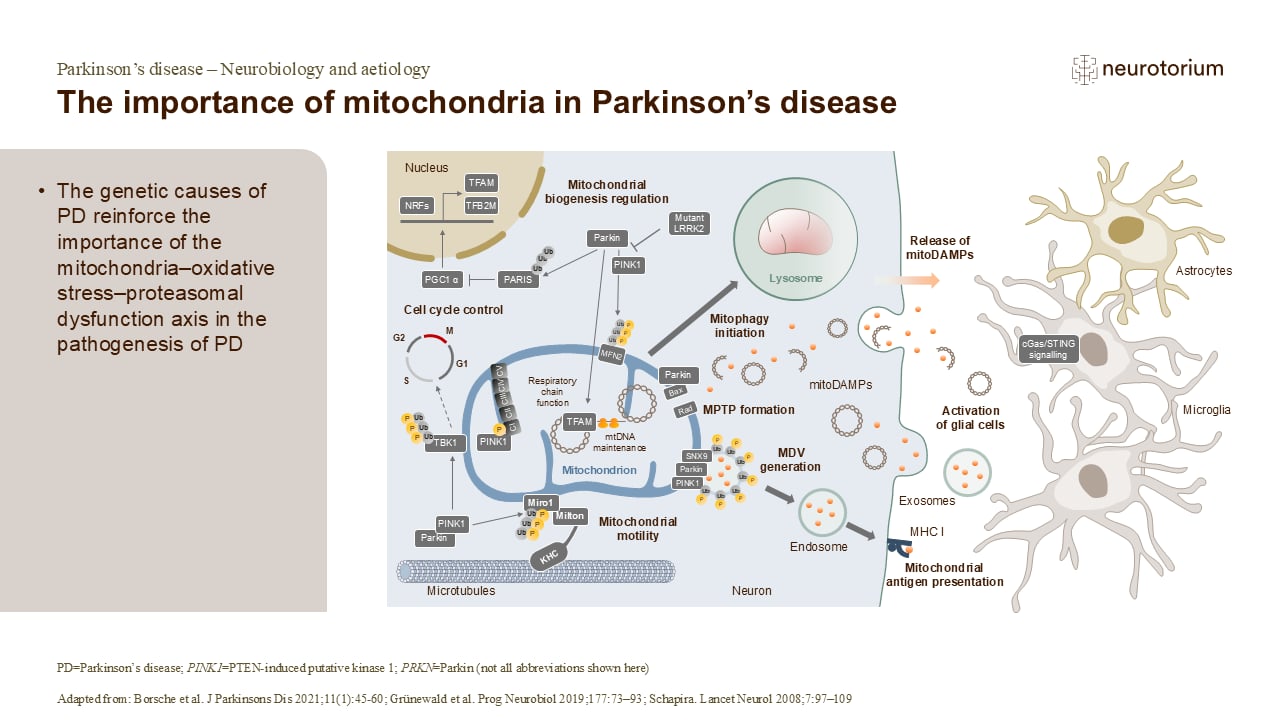
This slide deck covers the neurobiology and aetiology of Parkinson’s Disease. The foundational neurobiology underlying Parkinson’s disease is established alongside the routes of pathogenesis. Go to the slide deck.
Treatment Principles
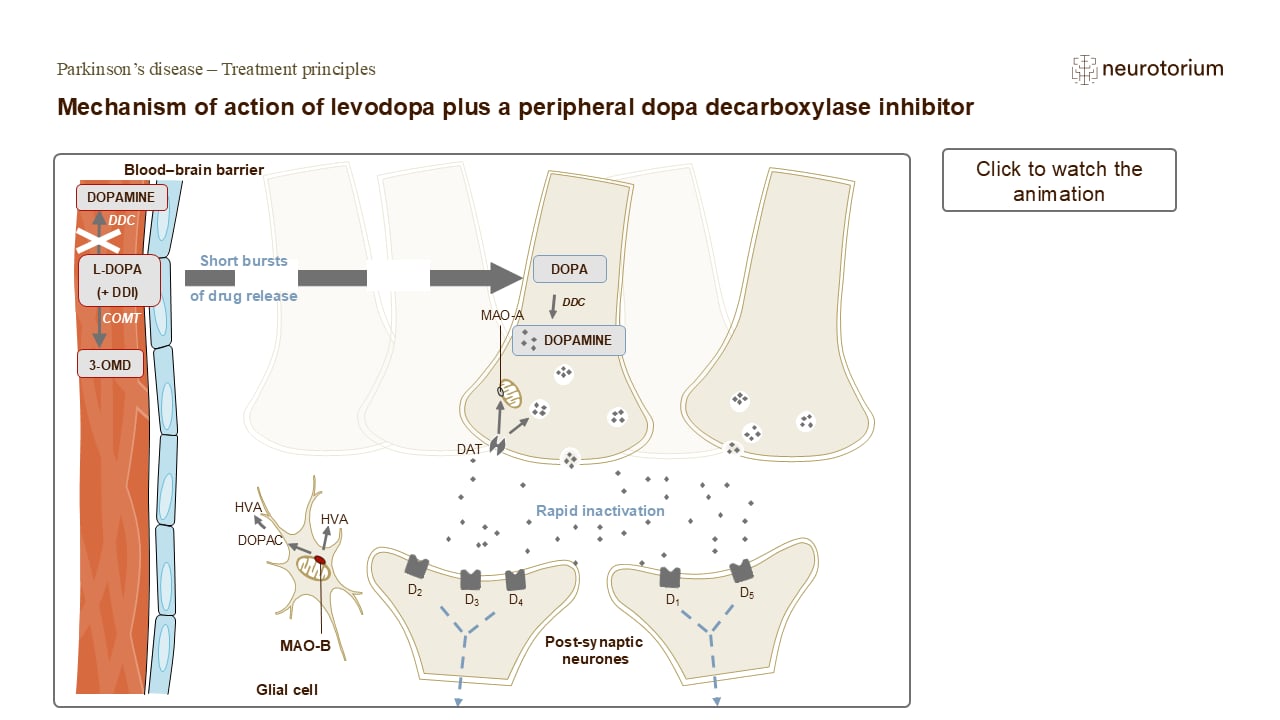
This slide deck covers current treatment options for Parkinson’s Disease. Information about a range of pharmacological, non-pharmacological, surgical approaches, as well as gene- and cell-based therapies are explored. Go to the slide deck.
Articles on Parkinson’s Disease
Our selected articles will delve into these facets of Parkinson’s disease, offering insights into the diverse nature of non-motor symptoms, their impact on patients, and the potential for improved management.

Genetics in Parkinson’s disease – coming to the fore of day-to-day clinical and research practice
This article discusses the major developments that have taken place in the PD genetics field, and provides an understanding of why and how genetics is increasingly being integrated into day-to-day clinical and research practice.
Body-First and Brain-First Parkinson’s Disease
This article reviews the body-first and brain-first model of Lewy body disease (BvB model), a theoretical framework that synthesises findings from clinical studies, epidemiology, animal models, and postmortem studies.
The microbiome-gut-brain axis in Parkinson’s disease
Evidence has been accumulating over the past years for a bidirectional relationship between the brain and the gut that plays an important role in Parkinson’s disease (PD).
Gastrointestinal dysfunction in Parkinson’s disease
It is now well recognised that gastrointestinal symptoms, particularly constipation, are amongst the most prominent and troublesome early manifestations of PD.
Watch the Videos on Parkinson’s Disease
Get insights on Parkinson’s disease through our videos. Understand the complexities of Parkinson’s Disease pathology and explore the mechanics of movement with The Brain Prize Explainer. Elevate your understanding with expertly curated content.
Brain-first vs Body-first Parkinson’s Disease
Professor Dr. Per Borghammer explains the brain-first vs body-first model of Parkinson’s disease, which consists of two distinct pathways of disease progression. Go to video.
Dopamine in Parkinson’s Disease and Schizophrenia
In this video, Professors Shen-Yang Lim and Christoph Correll discuss the crucial role of dopamine in both Parkinson’s disease and Schizophrenia. Go to video.
Understanding the pathology of Parkinson’s Disease
This video explores the pathology of Parkinson’s disease, focusing on the role of α-synuclein in its pathogenesis, the resulting motor dysfunction, and treatment options. Go to video.
Download Illustrations & Figures on Parkinson’s Disease
View an illustration of the bidirectional interplay between the brain and the gut, involving pathways such as the vagus nerve and bloodstream. Factors contributing to Parkinson’s disease development encompass aging-related processes, alpha-synuclein aggregation and spread, the gut bacterial microbiome and its metabolic activities, gut barrier integrity, inflammation, environmental influences, host genetic factors, and possibly chance effects. See a schematic illustration depicting how the gut-brain axis may contribute to the spread of alpha-synuclein pathology below.


Frequently Asked Questions (FAQ)
The information provided in this document is for educational purposes only and is not a substitute for medical care. If you have questions about your health, speak with a healthcare professional.
Parkinson’s disease (PD) is a chronic and progressively worsening condition that causes degeneration of nerve cells in the brain, impacting both motor and non-motor systems. This results in motor symptoms such as tremors, stiffness, slowness of movement, and gait and balance difficulties; and non-motor symptoms such as cognitive impairment, blood pressure issues, constipation, and sleep disorders.
References
PD is a neurodegenerative condition affecting the brain that primarily causes a loss of dopamineproducing brain cells in the substantia nigra. While the exact causes of PD are often multi-factorial, the aggregation of alpha-synuclein proteins in the brain is believed to play a major role, leading to the death of brain cells. However, the underlying reasons for these protein aggregations are complex and still under debate.
Besides ageing, which overall is the biggest risk factor for PD, researchers have found several environmental factors that are associated with PD development. These include pesticides and other environmental toxicants. Underlying genetic factors may also contribute substantially to PD risk. All these factors can act to disrupt normal cellular functions, such as mitochondrial function and autophagy (a process that helps clear out damaged parts of cells), contributing to the neurodegenerative process.
References
- Neurotorium. Parkinson’s Disease – Neurobiology and Aetiology. https://neurotorium.org/slidedeck/parkinsons-disease-neurobiology-and-aetiology/
- Dorsey, E. R. et al. Environmental toxicants and Parkinson’s disease: recent evidence, risks, and prevention opportunities. Lancet Neurol. 24, 976–986 (2025).
- Lim, S.-Y. et al. Uncovering the genetic basis of Parkinson’s disease globally: from discoveries to the clinic. Lancet Neurol. 23, 1267–1280 (2024).
- Simuni, T. et al. A biological definition of neuronal α-synuclein disease: towards an integrated staging system for research. Lancet Neurol. 23, 178–190 (2024).
As people live longer, the number of individuals with PD has grown and is projected to continue to grow substantially. In the past 25 years, the prevalence of PD has doubled. In 2019, global estimates showed that over 8.5 million people were living with PD – an accelerated increase that makes PD the world’s fastest-growing neurological disorder.
References
- Neurotorium. Parkinson’s Disease – Epidemiology and Burden. https://neurotorium.org/slidedeck/parkinsons-disease-epidemiology-burden/
- Dorsey, E. R. & Bloem, B. R. The Parkinson Pandemic—A Call to Action. JAMA Neurol. 75, 9–10 (2018).
- Parkinson disease. https://www.who.int/news-room/fact-sheets/detail/parkinsondisease.
PD is often recognised by its impact on movement (motor symptoms), but it also includes a range of other symptoms that can affect different non-motor aspects of daily life. The four key motor features are slowness of movement (bradykinesia), resistance to movement (muscular rigidity), shaking that occurs when muscles are relaxed (resting tremor), and challenges with balance (which might make the affected person more likely to fall, i.e., postural instability) and gait.
There are four major domains of non-motor symptoms. These include neuropsychiatric (including depression, anxiety, psychosis, impaired cognition, and dementia), sleep-related (such as dreamenacting behaviours or REM sleep behaviour disorder [RBD]), autonomic (including gastrointestinal, urinary, and sexual dysfunction; and orthostatic hypotension), and sensory (including pain and olfactory disturbance) features.
References
- Neurotorium. Parkinson’s Disease – History, Definitions and Diagnosis. https://neurotorium.org/slidedeck/parkinsons-disease-history-definitions-diagnosis/
- Bloem, B. R., Okun, M. S. & Klein, C. Parkinson’s disease. Lancet Lond. Engl. 397, 2284–2303 (2021).
- Postuma, R. B. et al. MDS clinical diagnostic criteria for Parkinson’s disease. Mov. Disord. Off. J. Mov. Disord. Soc. 30, 1591–1601 (2015).
PD is diagnosed primarily through a careful evaluation of the medical history, a clinical examination, and through observing how well symptoms improve with specific treatments and their evolution over time (months and years). There is currently no single test that can definitively diagnose PD, such as a blood test or genetic test, although there have been recent advances that put this within reach. Instead, doctors often use these methods to rule out other conditions that might mimic PD.
References
- Neurotorium. Parkinson’s Disease – History, Definitions and Diagnosis. https://neurotorium.org/slidedeck/parkinsons-disease-history-definitions-diagnosis/
- Fox, S. H. et al. International Parkinson and movement disorder society evidencebased medicine review: Update on treatments for the motor symptoms of Parkinson’s disease. Mov. Disord. Off. J. Mov. Disord. Soc. 33, 1248–1266 (2018).
- Berg, D. et al. Time to redefine PD? Introductory statement of the MDS Task Force on the definition of Parkinson’s disease. Mov. Disord. Off. J. Mov. Disord. Soc. 29, 454–462 (2014).
- Williams, D. & Litvan, I. Parkinsonian syndromes. Contin. Lifelong Learn. Neurol. 19, 1189–1212 (2013).
The primary emphasis in the care of individuals with PD should focus on maximising quality of life and reducing disability. Conventional medical and surgical therapies are still limited to providing only partial (although usually quite substantial) relief.
Levodopa is often the first treatment used for managing PD. Levodopa is a medication that increases dopamine levels in the brain. In the early stages of the disease, levodopa and similar medications typically work well, and the improvement in symptoms can be quite noticeable. However, as the disease progresses, the effectiveness of these medications might decrease, and their duration of action might become shorter. This ‘wearing-off’ phenomenon results in symptoms reappearing before the next dose of medication and is often accompanied by involuntary movements (dyskinesias) during ON periods when the medication is working. In some cases, these motor response complications may require device-aided treatments such as deep brain stimulation (DBS) or dopamine infusions.
The incorporation of allied healthcare professionals, such as specialist nurses, physiotherapists, and speech therapists, is essential to provide the best quality of care for patients with PD, aiming to support the patient and caregivers, maintain as much independence as possible, and prevent complications that can arise from the disease and treatments.
References
- Neurotorium. Parkinson’s Disease – Treatment Principles. https://neurotorium.org/slidedeck/parkinsons-disease-treatment-principles/
- Fox, S. H. et al. International Parkinson and movement disorder society evidencebased medicine review: Update on treatments for the motor symptoms of Parkinson’s disease. Mov. Disord. Off. J. Mov. Disord. Soc. 33, 1248–1266 (2018).
- Lim, S.-Y., Tan, A. H., Fox, S. H., Evans, A. H. & Low, S. C. Integrating Patient Concerns into Parkinson’s Disease Management. Curr. Neurol. Neurosci. Rep. 17, 3 (2017).
- Ypinga, J. H. L. et al. Effectiveness and costs of specialised physiotherapy given via ParkinsonNet: a retrospective analysis of medical claims data. Lancet Neurol. 17, 153–161 (2018).
- de Bie, R. M. A. et al. Update on Treatments for Parkinson’s Disease Motor Fluctuations – An International Parkinson and Movement Disorder Society Evidence- Based Medicine Review. Mov. Disord. Off. J. Mov. Disord. Soc. 40, 776–794 (2025).
While PD progresses gradually, it can eventually impact everyday activities, such as socializing, working, managing a home, and even the ability to perform self-care activities. Adjusting to these changes can be challenging. Joining support groups can provide emotional support, valuable information, and practical advice to help manage PD. Some also find individual or family counselling beneficial in developing coping mechanisms.
Staying informed about PD can be crucial, as it helps alleviate fear of the unknown and encourages active participation in health management. Many individuals with PD continue to work, albeit with modifications to their schedules and work environments to better manage and accommodate the symptoms. Engaging with available resources and making necessary adjustments can significantly aid in maintaining quality of life despite the challenges of PD.
References
- Neurotorium. Parkinson’s Disease – Treatment Principles. https://neurotorium.org/slidedeck/parkinsons-disease-treatment-principles/
- Parkinson’s Disease | National Institute of Neurological Disorders and Stroke. https://www.ninds.nih.gov/health-information/disorders/parkinsons-disease.
Autophagy is a process that helps clear out damaged parts of cells.
Bradykinesia refers to slowness of movements. Patients with PD often report feeling weak, slow, or clumsy, and this may be misinterpreted by family members as a ‘normal’ part of aging.
Degeneration refers to the irreversible loss of cells, tissues or organs, causing loss of normal structure and/or function over time.
Mitochondria are parts of cells (organelles) that produce the energy that the cells need to function.
Motor systems refer to the parts of the nervous system that coordinate muscle movement and control.
Muscular rigidity refers to resistance to changes in position. This symptom may sometimes be perceived by patients as stiffness or cramps.
Non-motor systems involve functions that are not related to physical movements, such as sense of smell and mental processing.
Orthostatic hypotension refers to a significant decrease in blood pressure that occurs when transitioning from a lying or sitting position to standing up, and can sometimes result in fainting spells.
RBD (REM Sleep Behavior Disorder) refers to a condition in which the person physically acts out his/her dreams (e.g., shout, punch, or kick) while in the REM stage of sleep.
The olfactory area is a brain structure associated with the sense of smell.
Tremor refers to an unintentional shaking of the body or a part of it (such as the hands).
References
- Bloem, B. R., Okun, M. S. & Klein, C. Parkinson’s disease. Lancet Lond. Engl. 397, 2284–2303 (2021).
- Simuni, T. et al. A biological definition of neuronal α-synuclein disease: towards an integrated staging system for research. Lancet Neurol. 23, 178–190 (2024).
- Williams, D. & Litvan, I. Parkinsonian syndromes. Contin. Lifelong Learn. Neurol. 19, 1189–1212 (2013).
- Mitochondria. https://www.genome.gov/genetics-glossary/Mitochondria.
- Glossary of Terms | Parkinson’s Disease. https://www.michaeljfox.org/glossaryterms.
- Autophagy: Definition, Process, Fasting & Signs. Cleveland Clinic https://my.clevelandclinic.org/health/articles/24058-autophagy.
- Orthostatic hypotension (postural hypotension) – Symptoms & causes – Mayo Clinic. https://www.mayoclinic.org/diseases-conditions/orthostatic-hypotension/ symptoms-causes/syc-20352548.
- Cleveland Clinic. REM Sleep Behavior Disorder: What It Is, Symptoms & Treatment. Cleveland Clinic https://my.clevelandclinic.org/health/diseases/24465- rem-sleep-behavior-disorder-rbd.